Why Anxiety Treatments May Not Work for Everyone
The short version
Anxiety treatments and support programmes do not work equally well for everyone. Outcomes can depend on the person's needs, the approach, how it is delivered, and other health or life factors. TRT™ is a structured, non-clinical therapy; the NHS Shropshire evaluation of the original programme reported a mean GAD-7 change from 18.28 to 2.84, but does not establish why scores changed or predict an individual's result.
Why Results Can Differ
Anxiety involves interacting processes, including threat appraisal, learned associations, attention, behaviour, and bodily arousal. Symptoms can also be influenced by health, sleep, stress, medication, and life circumstances. An approach may not meet someone's needs, may take time to help, or may need adjustment.
A clinician can review diagnosis, delivery, preferences, and other factors when support is not helping.
Psychological Therapies
Approaches such as CBT can help people recognise patterns in thoughts and behaviour and practise different responses. Treatment may include exposure or behavioural exercises, depending on the concern and plan. People can respond differently; if progress is limited, a qualified clinician can review the goals, formulation, delivery, or alternative options.
Exposure-Based Approaches
Exposure-based approaches are used for several concerns, including phobias, OCD, panic, and trauma-related problems; methods are adapted to the individual and condition. They involve planned practice with feared situations, sensations, or thoughts, often while reducing avoidance and safety behaviours.
A qualified clinician can discuss whether an exposure-based approach is appropriate and how to make it manageable.
Medication
Medication is one option for anxiety care, and a prescriber can discuss potential benefits, side effects, and suitability. People should not start, stop, or change prescribed medication on the basis of an online article. Withdrawal effects and symptom recurrence can overlap, so decisions should be made with the clinician who knows the person's history.
Other Approaches
People may also consider approaches such as hypnosis, EFT, or EMDR.
People may also consider approaches such as hypnosis, EFT, or EMDR. The evidence and recommendations differ by approach and condition. Separate questions include whether an approach improves a measured outcome and whether a proposed mechanism explains that improvement; evidence for one does not automatically establish the other.
People can ask providers about research quality, expected outcomes, and qualifications.
Evaluating Programme Claims
When comparing approaches, look for clearly described participants, measures, follow-up periods, and study design. A participant account, a pre–post change, and a controlled comparison answer different questions. Outcome measures can document change without identifying its cause; claims about a specific mechanism require evidence that measures that mechanism.
TRT™ Non-Clinical Therapy
TRT™ combines its cause-focused threat-recalibration model with a structured therapeutic process, education, practical recovery work and qualified support. It is non-clinical therapy, not merely an educational programme. The NHS Shropshire evaluation reported a cohort mean GAD-7 change from 18.28 to 2.84 (Z = −6.802, p < .001).
That result describes the evaluated participants' symptom scores; it is not a direct comparison with other approaches or evidence for a specific neural mechanism.
Finding a Suitable Next Step
If anxiety remains distressing or interferes with daily life, consider discussing it with an appropriately qualified professional. Review what has been tried, what outcomes matter, and whether other health or life factors need attention. The Institute offers non-clinical TRT™ therapy; it does not replace individual clinical assessment or care.
After recovery
Here is what actually changes
Participant accounts describe individual experiences. In the NHS Shropshire programme evaluation, mean GAD-7 scores changed from 18.28 at entry to 2.84 after the programme; this cohort average describes reported symptoms, not a guaranteed individual result or a measured neural mechanism.
Programme Outcome Evidence
NHS Shropshire Programme Evaluation · University of Copenhagen Analysis
Mean GAD-7 anxiety score: 18.28 → 2.84 (Z = −6.802, p < .001). Zero participants remained in the severe category post-program. 61 participants. Anxiety presentations included multiple diagnoses. Independently analysed results.
View full trial detailsCharles Linden · Founder, Institute of Applied Psychophysiology
"What actually happens in recovery is that your mind and body simply forget to be disordered."
Not gradually. Not partially. One day you notice the anxiety isn't there — not because you've learned to manage it, but because it's gone. Like it never existed.
People try to describe the moment and struggle to find words for it. The best most can offer is: "I just stopped thinking about it." The hypervigilance quietly switched off. The dread of the next attack stopped arriving. The compulsions became unnecessary and simply ceased.
This is not a metaphor. It is what the neuroscience predicts and what 650,000 recoveries confirm. When the subconscious threat response recalibrates to its correct baseline, there is nothing left to manage — because the source has changed.
Charles Linden experienced severe panic disorder, OCD, and agoraphobia for 27 years. He recovered permanently in 1996 — and has not experienced an anxiety disorder since.
His storyReal people. Real recoveries.
What recovery actually sounds like
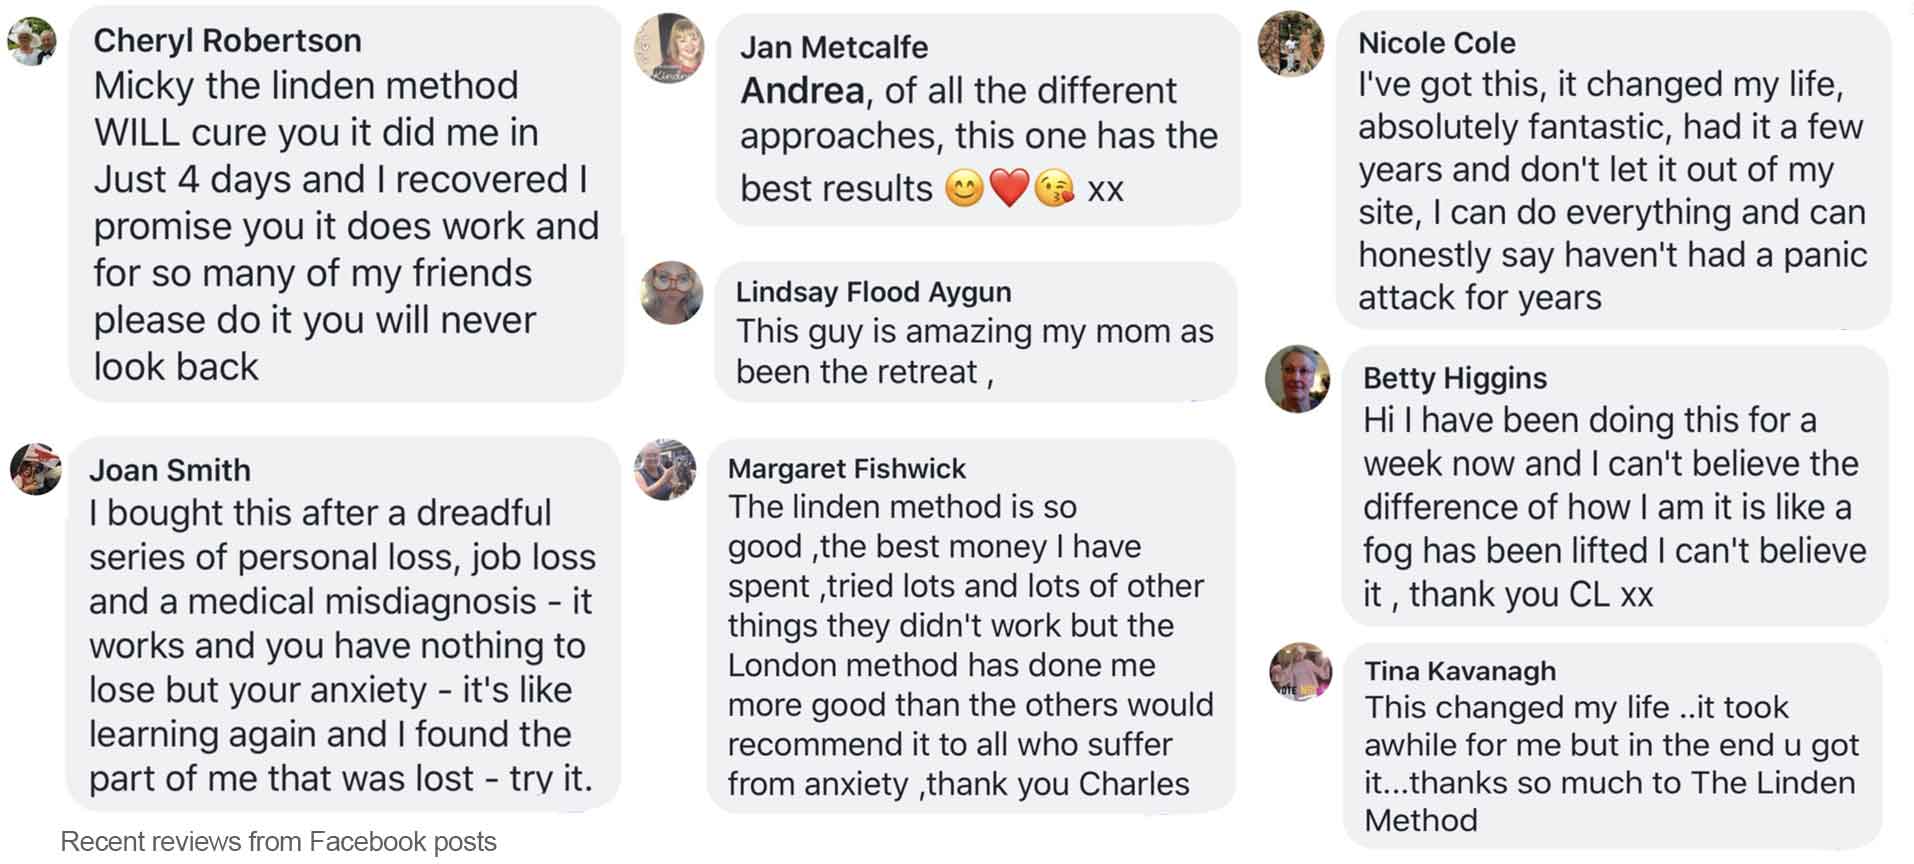
"I spent 12 years trying CBT, medication, and every therapy going. Nothing gave me my life back. Within six weeks of starting the program, I realised the anxiety was actually going — not being managed, not dulled. Gone."
Claire T.
Manchester · Panic Disorder
"I was housebound. My world had shrunk to my bedroom. TRT™ Therapy was the only thing that produced permanent results. Not coping strategies. Actual recovery. That was seven years ago and I have not looked back."
James R.
Edinburgh · Agoraphobia & Panic
"After my diagnosis I was put on medication and referred for CBT. Both helped a little. TRT™ Therapy did what neither could — it ended the anxiety completely. I cannot overstate how different my life is now."
Sarah M.
Leeds · GAD & OCD
"Suspend your disbelief. The belief will come when you feel the results."— Charles Linden, Founder of the Institute
Why conventional treatments cannot cure anxiety
Consider a smoke alarm. It detects danger and alerts you. When it works correctly, it is one of the most valuable safety systems in your home. Now imagine it gets stuck — firing not because there is danger, but because something in its mechanism has become miscalibrated.
This is, at its simplest, what anxiety disorder is. A safety system that has become miscalibrated. It fires when there is no threat. And it keeps firing.
Here is what every anxiety sufferer knows but what mainstream psychology has been slow to acknowledge: you cannot think your way out of a malfunctioning smoke alarm. You can learn to live with the noise. You can take medication that turns the volume down. But the alarm keeps sounding.
Every conventional anxiety treatment — CBT, medication, talking therapy, digital wellness apps — operates downstream of the source of the disorder. They target thoughts, beliefs, behaviours, and symptoms. None of them address the biological mechanism that produces and sustains the fear response.
This is not a failure of effort. It is a failure of focus. The correct problem was never solved.
Your body already knows how to do this
A fear response that never deactivated would have killed our ancestors. The switch exists. It is biological. It is in you.
Not a medical procedure. Not a drug. The deactivation mechanism is already yours — it just needs the right conditions to operate.
The only method developed specifically to activate the built-in deactivation mechanism. Not suppress. Not manage. Switch off — permanently.
CBT, medication, and talking therapy teach coping, suppress symptoms, or build frameworks. The underlying mechanism keeps firing. Relief is temporary. Relapse is common. The alarm never stops.
Creates the precise biological conditions under which the human fear response permanently deactivates. Not managed. Not suppressed. Switched off — by the body's own mechanism, exactly as evolution designed.
Thirty years. 650,000 recoveries. The data is unambiguous.
| Treatment | Relief rate | Relapse rate | Duration | Outcome |
|---|---|---|---|---|
| CBT | ~52% | 60%+ within 12 months | 12–24 months | Managed, not cured |
| SSRI Medication | ~45% | 60%+ on discontinuation | Indefinite | Suppressed, not resolved |
| Digital wellness apps | ~28% | High — avg. 8 weeks to dropout | Ongoing subscription | Engagement, not recovery |
| TRT™ Therapy | 100%* | Permanent — mechanism reset | 1–3 weeks average | Complete, permanent recovery |
The 100% recovery rate with compliance is not a marketing claim. It is the observed outcome of 30 years of direct recovery practice across 650,000 people globally. Every person who followed the method recovered. Without exception. The compliance qualifier reflects those who did not complete the process — not those who failed it.
100% recovery rate with compliance derived from thirty-year longitudinal outcomes data across 650,000 clients. Every participant who completed the protocol recovered. NHS-partnered GAD-7 evaluation recorded 84.5% symptom reduction at p<.001. Full clinical documentation available at instituteofappliedpsychophysiology.com/research
You don't have to be ready. You just have to begin.
The same mechanism that produces anxiety also creates resistance to its cure. An anxious brain is hypervigilant to anything unfamiliar. It flags change as potential danger. It pushes toward the familiar — even when the familiar isn't working — because familiarity feels safe.
This is why anxious people often resist the very process that will help them. It is not weakness. It is the disorder. Understanding this is the first step past it.
"If you are anxious and human, this process cannot fail."
— Charles Linden · Anxiety sufferer for 22 years. Recovered in 1996. Has helped 650,000 others do the same.The process works regardless of your scepticism. 650,000 people began unconvinced. They recovered anyway.
Waiting until you feel ready is itself a symptom of the disorder. The right time is now — because of biology, not courage.
Your immune system doesn't need your understanding to fight infection. Neither does the recovery mechanism.
The only way this doesn't work is if you don't do it. Follow the method. Biology takes care of the rest.
The belief comes with the results. Every person who recovered started exactly where you are right now.
Every person who followed the process recovered. The method has never failed anyone who did it. That is 30 years of data.
If you're anxious and human,
this process cannot fail.
You don't have to believe this yet. You don't have to feel ready. Suspend your disbelief. The belief comes with the results.
Begin your recovery todayScientific References & Evidence Base
NHS Shropshire Clinical Trial (2019)
Commissioned trial of TRT™ Therapy across all major anxiety condition diagnoses. Independently analysed by the University of Copenhagen. Mean GAD-7: 18.28 → 2.84, Z = −6.802, p < .001.
GAD-7 Validated Measure
Spitzer, R.L., Kroenke, K., Williams, J.B.W., & Löwe, B. (2006). A brief measure for assessing generalised anxiety disorder. Archives of Internal Medicine, 166(10), 1092–1097.
Threat Recalibration Therapy™ Methodology
Linden, C. (1996–present). Developed through 30 years of clinical application across 650,000 documented recoveries globally. Framework independently reviewed alongside NHS trial data.
Ready to recover?
650,000 people have permanently recovered. You already know why other treatments fail. Here is what works.
Structured TRT™ therapy, practical recovery work and qualified support. Non-clinical and non-prescribing.
CBT
£750–£3,000+
10+ sessions · relapse likely
Medication
£180–£600/yr
Ongoing · no drug made for anxiety
TRT™ Therapy
from £197
Once · permanent · guaranteed
🛡️ 60-day money-back guarantee · No questions asked
Key Numbers
CBT
One psychological treatment option
Medication
Discuss with a qualified prescriber
18.28 → 2.84
NHS evaluation cohort mean GAD-7
TRT™
Non-clinical therapy